


01
Excisions Coded on Lesion Size Alone
Malignant and benign excisions are sized by the lesion plus its narrowest margins. Code the lesion alone and an excision can pay a tier too low. We code from the full excised diameter.
Dermatology billing services built for how skin care actually gets paid: biopsies, excisions, Mohs surgery, dermatopathology and medical visits for California practices, with cosmetic services kept cleanly separate.
Every lesion, stage and specimen, billed and paid.
In dermatology, the claim is only as good as the measurement in the note. These five gaps can lead to repeated revenue loss.
Malignant and benign excisions are sized by the lesion plus its narrowest margins. Code the lesion alone and an excision can pay a tier too low. We code from the full excised diameter.
A skin check that leads to a biopsy needs modifier 25 and a separately documented problem. Without it, payers may bundle the visit. We apply it only when the note supports it.
Mohs is billed per stage and per tissue block over five, with the repair billed separately. We count stages and blocks and match the repair to the final defect.
A seborrheic keratosis billed as medical without symptoms can get denied; a medical lesion billed as cosmetic loses insurance revenue. We code to the documented reason and review ABN or self-pay requirements before service.
When the biopsy result changes the diagnosis, the claim must follow it. We link each specimen and 88305 to the final pathology diagnosis before billing.
Find your biggest revenue leak with a dermatology billing review.
Built around your care
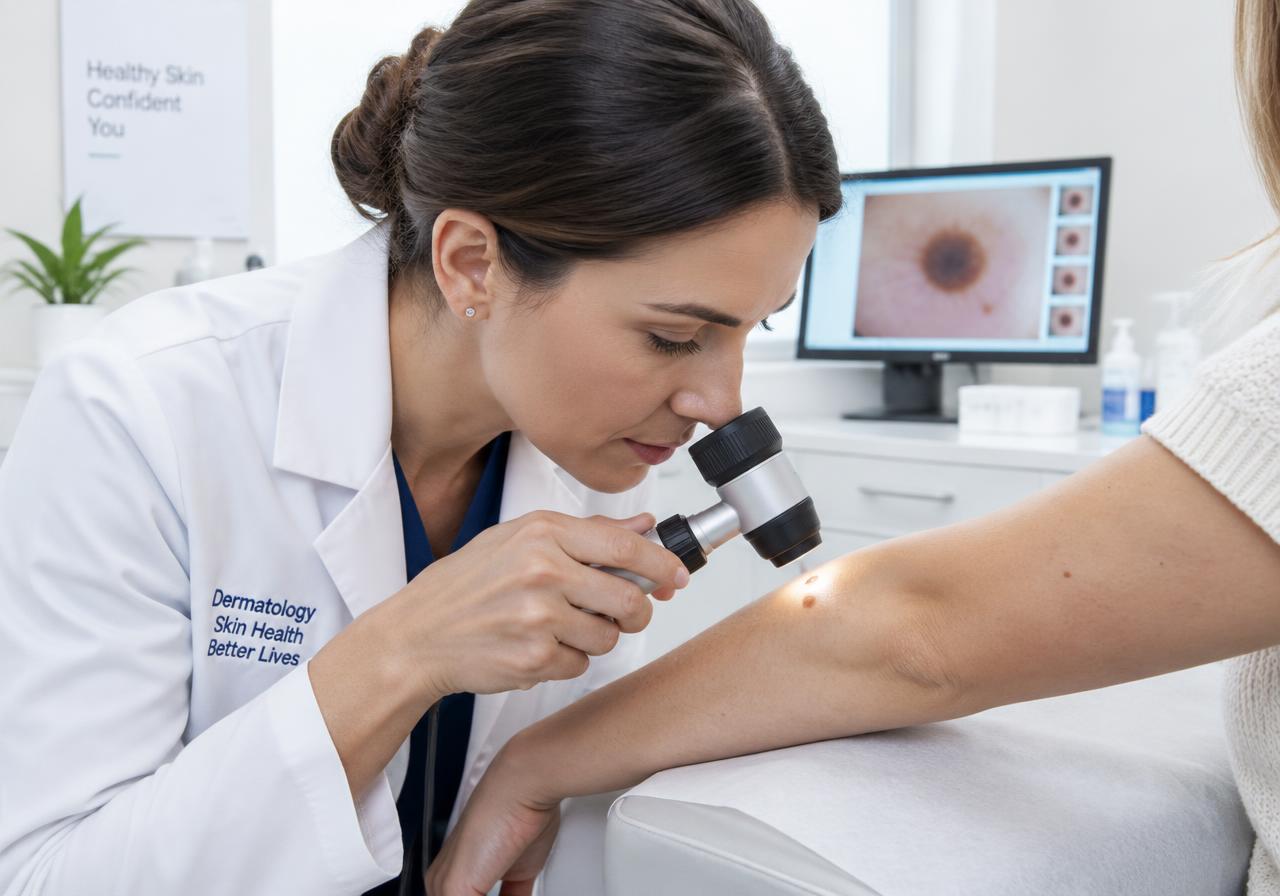
Your team focuses on biopsy, Mohs, excision and cosmetic visits. We handle the claims, payer follow-up and documentation questions behind them, so dermatology practices can spend less time chasing payments.
One accountable team from scheduling to final payment.
Coverage, deductibles and cosmetic exclusions reviewed before the visit.
Explore serviceAuthorization requirements for biologics, phototherapy, Mohs and surgical procedures tracked before service.
Explore serviceCPT, ICD-10-CM and modifiers coded from procedure notes and pathology reports.
Explore serviceClaims reviewed for lesion size, site, NCCI edits and global periods before submission.
Payments checked against your contracted rates to identify underpayments.
Denials worked by root cause and appeal deadline.
Explore serviceOpen claims worked by value, with old AR recovery scoped to your practice.
Explore servicePECOS, Medi-Cal PAVE, CAQH and commercial enrollment for dermatologists, PAs and NPs.
Explore serviceCosmetic estimates, Good Faith Estimates, statements and payment plans.
Dermatology-focused coding that checks lesion size, site, margins and pathology before a claim is built.
Service lines coordinated by one team, with cosmetic revenue tracked separately from insurance.
California-focused review of Noridian coverage policies, Medicare Advantage requirements and Medi-Cal Rx biologic rules.
One named contact who knows your providers, payers and front desk.
Reporting on collections, denials by root cause, AR aging and procedure-level reimbursement.
Discuss your rate, included services and contract terms based on provider count and service mix.
Medical, surgical and Mohs dermatology, coded to the lesion.
New and established visits (99202–99215), modifier 25 for separately documented same-day visits and procedures, and G2211 for eligible ongoing psoriasis, eczema and acne care.
Coded by technique, not size: tangential (11102/11103), punch (11104/11105) and incisional (11106/11107), with add-on codes for additional lesions.
Shave removals (11300–11313), benign excisions (11400–11471) and malignant excisions (11600–11646) by excised diameter and site, plus simple, intermediate and complex repairs (12001–13160), flaps (14000–14350) and grafts. Code selection follows the documented procedure, current code set and payer rules.
Actinic keratoses (17000, 17003, 17004), warts and benign lesions (17110/17111), and malignant lesion destruction (17260–17286).
First and additional stages by anatomic site (17311–17314), additional tissue blocks over five (17315), and same-day reconstruction, reviewed against coverage and appropriate use requirements.
88305, 88312 and 88342 billed globally for in-house labs or split into 26 and TC when appropriate, with each specimen linked to its final diagnosis.
Intralesional injections (11900/11901), I&D (10060/10061), nail procedures, phototherapy (96900–96912), excimer laser (96920–96922), photodynamic therapy (96567, 96573, 96574), patch testing (95044) and hyperhidrosis Botox (64650 + J0585).
Every diagnosis is coded to full specificity, from C44.311 basal cell carcinoma of the nose to L57.0 actinic keratosis.
The line between medical and cosmetic dermatology decides who pays. We draw it from the documentation, before the claim.
Coverage, authorization and claim routing reviewed for California practices.
Noridian JE local coverage rules for benign lesion removal and Mohs, plus plan-specific authorization requirements, including SCAN, Alignment, Humana and UnitedHealthcare Medicare Advantage.
Anthem Blue Cross, Blue Shield of California, Kaiser, Aetna and Health Net, plus Medi-Cal managed care requirements, with IPA and DOFR routing where applicable. Confirm your payer arrangements with our team.
Prior authorization and step therapy review for biologics such as dupilumab and IL-17/IL-23 inhibitors, through commercial plans and Medi-Cal Rx.
Review your Medicare, Medi-Cal and commercial payer requirements.
| Denial code | What it means | Typical dermatology cause | Our review |
|---|---|---|---|
| CO-16 | Missing information | Lesion size, site or path report missing | Pre-billing documentation check |
| CO-50 | Not medically necessary | Benign lesion removed without symptoms documented | Diagnosis and note reviewed before billing |
| CO-97 | Bundled service | E/M or repair bundled with excision | Modifier 25 or 59/XS only when supported |
| CO-4 | Modifier inconsistent or missing | Required modifier missing or inconsistent with the procedure | Modifier validation on each line |
| CO-151 | Frequency or number of services not supported | Repeat destruction or phototherapy exceeds supported frequency | Frequency rules and documentation checked |
| CO-197 | No authorization | Mohs, phototherapy or biologic without required approval | Authorization tracked before service |
Tired of the same denials every month?
The benchmarks we report on every month, by provider and procedure.
First-pass claims accepted without corrections.
Denials tracked by payer, procedure and root cause.
Time between billing and collection, reviewed month by month.
Aged balances prioritized for follow-up and resolution.
Collections measured against collectible revenue, with cosmetic revenue tracked separately.
| Modifier | Use in dermatology |
|---|---|
| 25 | Separate E/M on the day of a biopsy or procedure |
| 59 / XS | Distinct lesion or anatomic site when documentation and NCCI rules support separate billing |
| 57 | E/M that led to a major surgery decision |
| 58 / 78 / 79 | Staged, return or unrelated procedure in a global period, according to the documented circumstances |
| RT, LT, E1–E4, FA–F9, TA–T9 | Side, eyelid, finger or toe |
| GA / GZ / GX | Applicable Medicare notice and coverage status for non-covered or potentially non-covered services |
Modifier selection follows the documented lesion, procedure, notice status and applicable payer edits.
A coordinated billing team without building an in-house department.
MD, PA and NP billing with provider-level reporting.
Stage, block and reconstruction billing matched to documentation.
High-volume visits, biologics and chronic skin disease.
Global or split 88305 billing with clean specimen linkage.
Insurance and cosmetic revenue kept separate across locations.

A team that knows your specialty
Coders and billers familiar with dermatology workflows review every claim before it goes out and keep you updated with clear monthly reporting.
Old AR is worked in parallel while new claims start with us.
Review claims, denials and AR to identify missed revenue.
Agree on BAA requirements and EHR, pathology lab and payer portal access.
Prepare contracted California payer schedules alongside your cosmetic price list.
New claims start with us while prior AR is worked down.
Coordinate claim submission and your dedicated account manager.
Review collections, denials and procedure-level reimbursement with your providers.
Discuss a percentage-of-collections arrangement tailored to your practice. Confirm your rate, included services and contract terms with our team.
Practice-specific quote
Practice-specific quote
Practice-specific quote
Discuss Mohs, dermatopathology, pre-billing review and old AR recovery with our team. Confirm included services and how cosmetic collections are treated before choosing a plan.
| Consideration | In-house biller | California Billing Services |
|---|---|---|
| Cost | Salary, benefits, software, clearinghouse | Practice-specific billing quote |
| Dermatology coding depth | Depends on your hiring and training | Dermatology-focused review of excisions, Mohs and pathology |
| PTO and turnover | Internal coverage arrangements needed | Team-based workflow and continuity planning |
| Cosmetic vs medical separation | Depends on practice workflows | Separate workflows and reporting |
| Denial follow-up | Depends on available staff capacity | Root-cause and deadline-driven work queues |
Working inside the platforms you already use





System availability and access depend on the practice's current configuration and permissions.
Plus Orange County, the Inland Empire and Palm Springs.
HIPAA and CMIA-aligned data handling, a Business Associate Agreement and controlled access are central to billing setup. Review role-based access, encryption and audit-trail requirements with our team before sharing practice data, including clinical photos.
Pricing depends on provider count, claim volume, service mix and the scope of your plan. Contact our team to confirm your rate, included services and treatment of self-pay cosmetic revenue.
Can't find what you're looking for? Contact our billing specialists
Review under-coded excisions, missed Mohs blocks, bundling denials, underpayments by payer and aging AR with our team. Discuss the scope of your dermatology billing audit before sharing claims.